Antibiotics are a bedrock of modern medicine. But in the very near future, we're going to have to learn to live without them once again. And it's going to get nasty
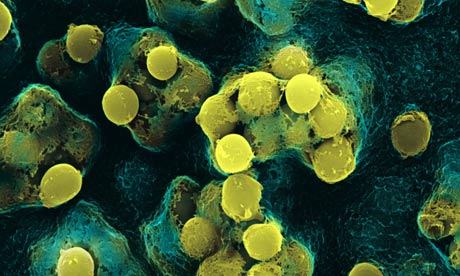
Streptococcus pyrogens bacteria. Photograph: S Lowry/University of Ulster/Getty Images
Just 65 years ago, David Livermore's paternal grandmother died following an operation to remove her appendix. It didn't go well, but it was not the surgery that killed her. She succumbed to a series of infections that the pre-penicillin world had no drugs to treat. Welcome to the future.
The era of
antibiotics is coming to a close. In just a couple of generations, what once appeared to be miracle medicines have been beaten into ineffectiveness by the bacteria they were designed to knock out. Once, scientists hailed the end of infectious diseases. Now, the post-antibiotic apocalypse is within sight.
Hyperbole? Unfortunately not. The highly serious journal
Lancet Infectious Diseases yesterday posed the question itself over a paper revealing the rapid spread of multi-drug-resistant bacteria. "Is this the end of antibiotics?" it asked.
Doctors and scientists have not been complacent, but the paper by Professor Tim Walsh and colleagues takes the anxiety to a new level. Last September, Walsh published details of a gene he had discovered, called NDM 1, which passes easily between types of bacteria called enterobacteriaceae such as
E. coli and
Klebsiella pneumoniae and makes them resistant to almost all of the powerful, last-line group of antibiotics called carbapenems. Yesterday's paper revealed that NDM 1 is widespread in India and has arrived here as a result of global travel and medical tourism for, among other things, transplants, pregnancy care and cosmetic surgery.
"In many ways, this is it," Walsh tells me. "This is potentially the end. There are no antibiotics in the pipeline that have activity against NDM 1-producing enterobacteriaceae. We have a bleak window of maybe 10 years, where we are going to have to use the antibiotics we have very wisely, but also grapple with the reality that we have nothing to treat these infections with."
And this is the optimistic view – based on the assumption that drug companies can and will get moving on discovering new antibiotics to throw at the bacterial enemy. Since the 1990s, when pharma found itself twisting and turning down blind alleys, it has not shown a great deal of enthusiasm for difficult antibiotic research. And besides, because, unlike with heart medicines, people take the drugs for a week rather than life, and because resistance means the drugs become useless after a while, there is just not much money in it.
Dr Livermore, whose grandmother died for lack of infection-killing drugs in 1945, is director of the antibiotic resistance monitoring and reference laboratory of the
Health Protection Agency. Last year, the HPA put out an alert to medical professionals about NDM 1, urging them to report all suspect cases. Livermore is far from sanguine about the future.
"A lot of modern medicine would become impossible if we lost our ability to treat infections," he says. He is talking about transplant surgery, for instance, where patients' immune systems have to be suppressed to stop them rejecting a new organ, leaving them prey to infections, and the use of immuno-suppressant cancer drugs.
But it is not just an issue in advanced medicine. Antibiotics are vital to abdominal surgery. "You safeguard the patient from bacteria leaking into the body cavity," he says. "If you lose the ability to treat these infections, far more people would die of peritonitis." Appendix operations would carry the same risk as they did before Fleming discovered penicillin in 1928.
It may not be over yet, he says, but "we are certainly scraping the bottom of the barrel to find antibiotics that are effective against some of the infections caused by bacteria."
Running out is not the only issue, he says. When somebody has a severe infection – say blood poisoning – causing a high fever, a hospital clinician will dispatch blood samples to the lab to find out exactly what he is dealing with. But that takes time. "He will start you on antibiotics because that will kill infection within 48 hours," says Livermore. "So during 48 hours, you are being treated blind. The more resistant your bacteria are, the less likely the antibiotic is going to work."
Studies have shown, he says, that the chances of dying from hospital pneumonia or septicaemia (blood poisoning) are twice as high if the bacteria are drug-resistant, rising in the case of pneumonia from 20-30% to 40-60%.
For a long time now, doctors have known they were in a race to stay a few steps ahead of the rapidly growing resistance of bacterial infections to antibiotics. Ten years ago, the so-called superbug MRSA caused front-page panic. Hospital patients were picking up
Staphylococcus aureus infections that were resistant to the hitherto powerful antibiotic methicillin. All-out war, led by the government's former chief medical officer Sir Liam Donaldson, against MRSA and also
C. diff (
Clostridium difficile) has reduced the threat of what are known as Gram-positive bacteria. Hospital hygiene has been massively stepped up and, in response in part to public anxiety, pharmaceutical companies have put money into finding new antibiotics for those infections.
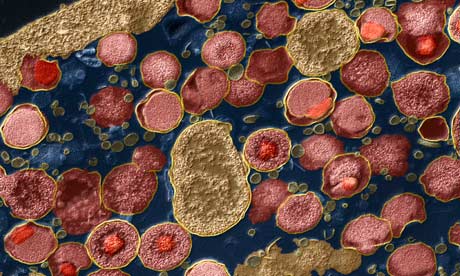
Chlamydia trachomatis bacteria. Photograph: Eye of Science/Science Photo Library
But it's like putting a finger in a hole in the dam, only to find the water surges out somewhere else. Bacteria are great survivors. The biggest threat now, experts believe, is from multi-drug-resistant Gram-negative bacteria, such as NDM 1-producing enterobacteriaceae
and an enzyme called KPC which has spread in the US (and in Israel and Greece) which also gives bacteria resistance to the carbapenems, the most powerful group of antibiotics we (once) had.
"The emergence of antibiotic resistance is the most eloquent example of Darwin's principle of evolution that there ever was," says Livermore. "It is a war of attrition. It is naive to think we can win."
So the game now is to keep bacteria at bay. Hygiene is an obvious weapon. Better cleaning, hand gels and stern warnings to staff and public alike have helped reduce infection rates in hospitals. But Professor Richard James, director of the
centre for healthcare associated infections at the University of Nottingham, warns that bugs don't stay in hospitals (indeed, the NDM 1- producing bacteria appear to be widespread in the community in India, passed on through contaminated water, in which people bathe, wash clothes and also defecate).
"The worry is once these organisms are out in the community," says James. "There probably is some need for public education about infection and, for instance, kitchen hygiene when you are cooking. People of my generation were taught a lot about washing your hands before every meal. It was automatic that it was done. A lot of that has gone." There are some innovative ideas about, he says, on ways of teaching children in school to wash their hands – in the hope that they will then go home and pester their parents to do the same.
Beyond that, there is a real need to conserve those antibiotics we have. "To me, it has many parallels with the problems of energy in economies around the world," he says. Carbon trading was dreamed up to try to conserve oil and reduce its pollutant effects. There have now been a couple of interesting papers suggesting a Pigouvian tax – which he defines as one levied on an agent causing an environmental problem as an incentive to mitigate that problem – for antibiotics.
Like oil, he points out, antibiotic usefulness is finite. And the cost of drug resistance is not reflected in the price of the drug. "If you consider antibiotic sensitivity as a resource like oil, you want to maintain that by introducing a tax," he says. It would be worldwide and the proceeds could fund new drug development.
But should you tax life-saving drugs, especially in poor countries? "If you don't do anything, there won't be any antibiotics anyway," says James starkly. "At least it is a suggestion of something that could be done."
If anybody had doubted it for a moment, Walsh's paper shows that neither the UK nor any other country can pull up the drawbridge. "This report shows that the battle to control the emergence of antibiotic-resistant superbugs through appropriate use of antibiotics must be fought at an international level," says Kevin Kerr, consultant microbiologist at Harrogate district hospital. "It illustrates the importance of considering health issues as a world issue – how antibiotics are prescribed and controlled in one part of the world can very rapidly have consequences elsewhere," says Christopher Thomas, professor of molecular genetics at the University of Birmingham.
"Frankly, pharmaceutical companies as well as governments and the European Commission need to really get their act together," says Walsh, who has been urging co-ordinated efforts across the world to put in place good surveillance systems to find out what resistance is developing and where, and then look for interventions. He had Columbia, Mexico, Thailand and India all willingly on board for one surveillance scheme, but the European Commission would not fund it. "What we need is for somebody to give us something like €3m [£2.5m] a year. It's not a lot of money."
The fact is that many people have still got their heads in the sand. But soon we will start seeing patients in NHS hospitals whose infections won't clear up. In the battle for survival of the fittest between human beings and bacteria, just now it looks as though the best we are going to get is a draw – if we are lucky.
After antibiotics: what happens when the drugs don't work
• Transplant surgery becomes virtually impossible. Organ recipients have to take immune-suppressing drugs for life to stop rejection of a new heart or kidney. Their immune systems cannot fight off life-threatening infections without antibiotics.
• Removing a burst appendix becomes a dangerous operation once again. Patients are routinely given antibiotics after surgery to prevent the wound becoming infected by bacteria. If bacteria get into the bloodstream, they can cause life-threatening septicaemia.
• Pneumonia becomes once more "the old man's friend". Antibiotics have stopped it being the mass-killer it once was, particularly among the old and frail, who would lapse into unconsciousness and often slip away in their sleep. Other diseases of old age, such as cancer, have taken over.
• Gonorrhea becomes hard to treat. Resistant strains are already on the rise. Without treatment, the sexually transmitted disease causes pelvic inflammatory disease, infertility and ectopic pregnancies.
• Tuberculosis becomes incurable – first we had TB, then multi-drug-resistant TB (MDR-TB) and now there is XDR-TB (extremely drug resistant TB). TB requires very long courses (six months or more) of antibiotics. The very human tendency to stop taking or forget to take the drugs has contributed to the spread of resistance.